

A good breast augmentation candidate is a healthy adult with fully developed breasts, realistic goals, and a personal desire to increase breast volume or improve proportion. She should not be pregnant or breastfeeding, should have no active breast infection or untreated breast condition, and should be willing to follow the restrictions required for safe healing.
Candidacy involves more than qualifying medically. Breast anatomy, skin quality, nipple position, lifestyle, implant expectations, and future pregnancy plans all help determine whether augmentation alone can create the desired result.
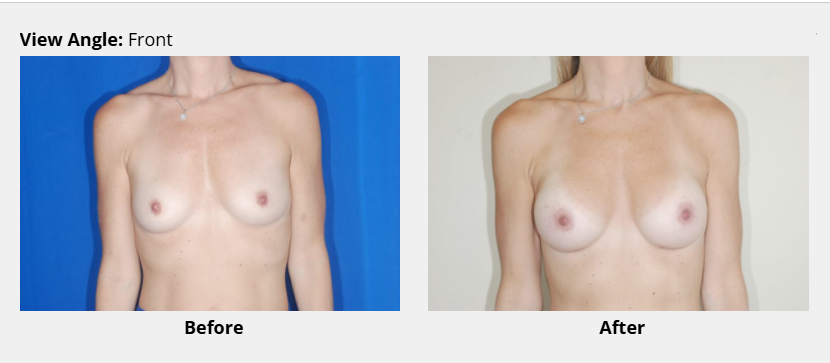
What Goals Can Breast Augmentation Address?
Breast augmentation increases breast volume with implants. It may be appropriate if you want fuller breasts, more upper-breast fullness or projection, better proportion between the breasts and the rest of the body, restoration of volume lost after pregnancy or weight change, or improvement of certain size differences between the breasts.
The operation can make a subtle or more noticeable change. The appropriate implant is selected according to the patient’s anatomy and desired appearance rather than a universal ideal size.
What Health Factors Affect Candidacy?
Good candidates are generally healthy enough for anesthesia and elective surgery. Medical conditions should be stable, breast imaging should be current when appropriate, and there should be no active infection, untreated breast cancer, or unresolved breast finding.
Smoking and nicotine impair blood flow and increase wound-healing risks. A patient who uses nicotine must be willing to stop according to Dr. Bogue’s preoperative and postoperative instructions. Medications, supplements, prior operations, allergies, bleeding history, and previous anesthesia problems are reviewed during consultation.
Why Do Realistic Expectations Matter?
Implants can increase breast volume and influence shape, but they cannot produce perfect symmetry or guarantee a cup size. Natural differences in the chest wall, ribs, breast tissue, nipples, and skin remain relevant after surgery.
Breast implants are not lifetime devices. A patient should be comfortable with long-term follow-up, the possibility of future imaging, and the possibility that revision or removal may eventually be needed because of rupture, capsular contracture, implant movement, tissue change, or a change in personal preference.
Can an Implant Correct Sagging?
An implant can fill a breast that has lost volume, but it does not reliably correct significant breast or nipple descent. If the nipple sits low or the breast tissue has stretched substantially, adding a breast lift may provide a better and more stable shape.
Many first-time augmentation patients do not need a lift. Borderline cases require examination because choosing an implant that is too large simply to avoid a lift can create an unattractive or less stable result.
Does Breast Asymmetry Prevent Augmentation?
No. Mild asymmetry is normal, and augmentation can often improve a noticeable size difference by using different implant volumes or profiles. The surgical plan may also require a lift, reduction, or another adjustment on one side when the breasts differ in shape or nipple position as well as size.
Perfectly identical breasts are not a realistic expectation. Dr. Bogue identifies which differences can be improved and which arise from the chest wall or other anatomy that an implant cannot change.
Should You Wait Until After Pregnancy?
Future pregnancy does not automatically disqualify someone from augmentation, but pregnancy and breastfeeding can change breast volume, skin, and nipple position. A patient planning pregnancy soon may prefer to postpone surgery to reduce the chance that these changes alter the result.
Many women with implants can breastfeed, although any breast surgery can affect milk production in some patients. Discuss future pregnancy and breastfeeding goals before the incision and implant plan are finalized.
Are You Prepared for Recovery?
A suitable candidate can arrange transportation, help at home, time away from strenuous responsibilities, and adherence to postoperative restrictions. Activity remains very light for the first two weeks, without exercise or heavy lifting. Cardio, light lifting, and full arm range of motion can usually resume at about two weeks.
A supportive or compression bra is typically worn around the clock for six weeks. Most patients can return to unrestricted activity around six weeks after clearance. Patients with implants beneath the pectoralis muscle also need to modify heavy chest exercise over the long term because repeated muscle forces can contribute to implant displacement.
How Are Implant Size and Placement Chosen?
Dr. Bogue uses a biodimensional approach, selecting an implant that fits the breast and chest rather than relying on volume alone. Width, projection, gel cohesivity, existing tissue, skin, and the preferred look all matter. The Arbrea 3D Simulator and Mentor sizing system help patients compare options during consultation.
For many patients, Dr. Bogue prefers subfascial placement above the pectoralis muscle but beneath its fascial covering. Dual-plane placement may be useful when additional tissue coverage is needed. The choice depends on implant type, tissue thickness, lifestyle, and aesthetic goals.
When Might Another Procedure Be More Appropriate?
A lift may be more appropriate when the main concern is sagging rather than volume. A breast reduction is designed for breasts that feel too large or heavy. Existing implants with rupture, contracture, movement, or another problem require implant revision rather than a first-time augmentation.
The purpose of consultation is to determine whether an implant addresses the actual concern and, if so, which plan is proportionate and supportable by the patient’s tissues.
Cosmetic surgical consultations are $100 and the fee is credited toward surgery when booked. Call 561-886-1000 or request a consultation online.